
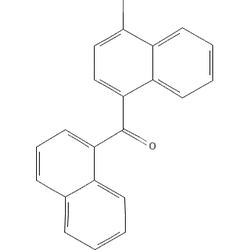
CB-13 Stats & Data
CCCCCOc1ccc(C(=O)c2cccc3ccccc23)c2ccccc12RSUMDJRTAFBISX-UHFFFAOYSA-NMeasured Affinities
Guide to PHARMACOLOGYMeasured binding and functional data for CB-13, curated by the IUPHAR/BPS Guide to PHARMACOLOGY. Each row cites the paper it came from. Lower concentrations mean tighter binding — a value in the sub-nanomolar range indicates a very potent interaction.
| Target | Action | Measure | Value | Concentration | Species | Source |
|---|---|---|---|---|---|---|
| CB2 receptor CNR2 | Agonist | pKi | 7.72 | 19.05 nM | Human | PMID 22284817 |
| CB1 receptor CNR1 | Agonist | pKi | 7.46 | 34.67 nM | Human | PMID 22284817 |
Reading this. pKi, pEC50 and pIC50 are negative log molar values, so a higher number means a tighter interaction; the concentration column converts them for you. Values from non-human species are laboratory measurements and do not translate directly to human effect. Receptor affinity is not a dose — it describes what a molecule binds, not how much of it is safe to take.
Receptor data from the IUPHAR/BPS Guide to PHARMACOLOGY (v2026.2), licensed CC BY-SA 4.0. Matched to this substance by InChIKey.
Effect Profile
CuratedModerate visuals with mild headspace and auditory effects, low body load
Tolerance & Pharmacokinetics
drugs.wikiTolerance Decay
Acute tolerance: develops within a single session — the reset numbers above apply after sustained heavy use, not after one binge. Within-session tachyphylaxis usually resets largely overnight.
Based on cannabinoid-class tolerance patterns: repeated daily activation downregulates CB1 signaling with partial reversal over days to weeks. Data specific to CB‑13 in humans are lacking; values above are heuristic. Evidence quality: anecdotal and cannabinoid-class extrapolation.
Cross-Tolerances
Harm Reduction
drugs.wiki• Identity warning: “CB‑13” refers to at least two unrelated cannabinoids in the literature. Recreational markets and some lists use “CB‑13” for a naphthoyl–naphthyl ketone, while pharmacology papers use CB‑13 = SAB‑378 (peripherally restricted CB1/CB2 agonist). Verify you have SAB‑378; misidentification increases risk.
• Peripherally restricted does not guarantee zero central effects: very high plasma levels or BBB changes (e.g., illness, co-intoxication) can allow some CNS penetration, so treat impairment as possible at higher doses. This is a general BBB principle for peripherally targeted drugs.
• Cannabinoids can cause tachycardia and lower blood pressure; standing up quickly may cause light-headedness or fainting. Sit/lie down if dizzy; avoid combining with other vasodilators (e.g., poppers, PDE5 inhibitors).
• Avoid driving or hazardous tasks until fully sober and well rested; cannabis-like agents are associated with increased motor vehicle crash risk, especially when combined with alcohol. A conservative minimum of 6–8 h is advisable after oral dosing.
• If acquired as an unlabeled powder, consider laboratory drug checking (GC/MS, LC/MS) to confirm identity/purity. Note some services do not accept cannabis/cannabinoid products, but may analyze powders.
• Smoking/vaping synthetic cannabinoids has historically led to uneven dosing and ‘hot pockets’ in herbal blends; if vaporizing neat material, use the lowest effective temperature and small test puffs to reduce pyrolysis exposure. Avoid homemade sprayed herbal products.
• Start with an allergy test (e.g., ≤25 mg oral or ≤5 mg vapor) due to unknown excipients and the absence of formal human safety data; increase in small steps with long waits (≥2–3 h oral; ≥45–60 min inhaled) before redosing. Rationale: unregulated supply variability and cannabinoid interindividual sensitivity.
• Combining with CNS depressants (alcohol, opioids, benzodiazepines, sedating antihistamines) markedly increases sedation and accident risk; with opioids and/or gabapentinoids the risk of respiratory depression is higher than either alone.
• Expected effects are mostly peripheral (analgesia, anti-inflammatory, body relaxation, mild warmth) with relatively muted classic cannabis ‘high’; users often report sedation and dry mouth, and at higher doses nausea or orthostatic symptoms.
• Legal and market shifts can lead to mislabeling with other potent synthetic or semi-synthetic cannabinoids; variable potency between batches is well-documented. Test a new batch cautiously.
References
Cited references
- National Academies (2017) – Injury and Death: motor vehicle crashes and cannabis
- PDQ Cannabis and Cannabinoids – Side effects (tachycardia, hypotension, sedation)
- StatPearls – Cannabinoid Toxicity (physiologic effects; risks with synthetic cannabinoids)
- EUDA (EMCDDA) – Synthetic cannabinoids NPS market and variability
- EUDA European Drug Report 2025 – NPS & semi-synthetic cannabinoids
- Toronto Drug Checking Service – About (methods)
- Toronto Drug Checking Service – Understanding your results (LC/GC-MS)
- Reddit r/IBSResearch – discussion of mouse data showing CB‑13 peripheral analgesia and tolerance with MOR synergy (contextual user resource)
- UNODC/EMCDDA report list including CB‑13 entry (nomenclature collision context)